Revolutionary Psoriasis Treatment Protocols Promise Superior Skin Clearance by 2026
October 2, 2026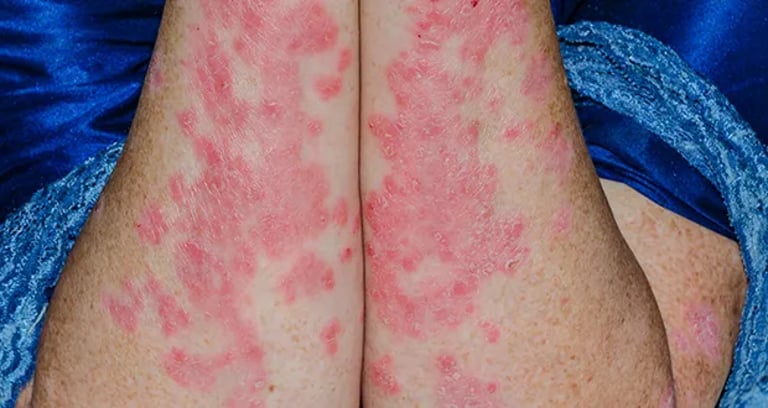

A patient-friendly, dermatology-backed workflow starts with confirming the psoriasis diagnosis, assessing its impact, screening for psoriatic arthritis and comorbidities, optimizing topical treatments, and referring early for systemic therapies or phototherapy when appropriate, while coordinating baseline labs and vaccinations with dermatology.
Drug choices should be guided by comorbidities, such as preferring IL-23 or ustekinumab in patients with inflammatory bowel disease, avoiding or closely monitoring IL-17 agents in those with recurrent candidiasis or IBD risk, and planning pregnancies by avoiding methotrexate and acitretin, with growing safety data for many biologics in pregnancy.
By 2026, modern therapies can achieve PASI90–PASI100 skin clearance, with IL-23/IL-17 inhibitors providing superior clearance and durability, and deucravacitinib offering an effective oral option.
Baseline and follow-up monitoring for systemic or biologic therapy should include infection screening (TB, hepatitis B/C, HIV), vaccination status, CBC, LFTs, kidney function, lipids, glucose, and pregnancy testing where relevant, with evolving guidance on live versus non-live vaccines.
Systemic options are tailored to the patient and include conventional non-biologics (e.g., methotrexate, ciclosporin, acitretin), phototherapy (NB-UVB, PUVA), targeted oral agents (apremilast, deucravacitinib), and biologics (IL-23/IL-17/IL-12/23 inhibitors, TNF inhibitors); essential pre-immunosuppression steps include baseline labs, infection screening, and vaccination.
Psoriasis affects about 2% of people and is linked with cardiovascular disease, psoriatic arthritis, metabolic syndrome, NAFLD, and mental health issues, with the overall burden rising with skin severity.
Severity assessment should integrate body surface area, involvement of special areas, DLQI, and patient-reported impact; combining BSA, PGA, and DLQI can guide referrals and decisions on systemic therapy.
Important comorbidity screenings include PsA via PEST, cardiovascular/metabolic risk factors (BP, lipids, HbA1c, smoking, weight), mental health screening, and liver/metabolic risk (NAFLD) to inform drug choice and baseline labs.
In primary care, first-line management focuses on optimized topical therapy and avoiding routine systemic corticosteroids; refer to dermatology when BSA exceeds 10%, there is involvement of special areas, DLQI ≥10, topical failure, recurrent erythroderma, troublesome nail disease, suspected PsA, or need for rapid escalation.
Communicate patient-focused messages about psoriasis’ links to heart health and mood, set realistic goals like near-clear skin, and discuss joint, bowel symptoms, infections, pregnancy considerations, and vaccines.
Summary based on 1 source
Get a daily email with more Science stories
Source
Irish Medical Times • Oct 2, 2026
Moderate–to–severe plaque psoriasis – Modern management for GPs